









Healthcare websites convert at an average of 5.6%, with top performers reaching as high as 21.1%. A realistic target depends on your clinic, traffic, and conversion definition, with dedicated landing pages often performing better than general site traffic. We use these figures, alongside 50th, 75th, and 90th percentile benchmarks, to inform our audits.
TL;DR:
- Use the 50th percentile as your baseline, the 75th as a quarterly target, and the 90th only as a stretch goal for a specific campaign.
- Count calls alongside form submissions, then judge performance by booked and kept appointments per visit rather than by leads alone.
- Compare results by channel, device, specialty, and audience, because mobile forms, competition, and longer elective care decisions can depress blended rates.
- Prioritize pages tailored to each campaign, shorter mobile forms, and faster lead response before buying traffic; use appointment attribution to identify which channels fill calendars.
Table of Contents
- Benchmarks at a Glance: Core Numbers and What “Top Performer” Looks Like
- Benchmarks by Channel: Paid Search, Organic Search, Email, and Direct Traffic
- Conversion Types and How Benchmarks Differ: Forms, Calls, and Booked Appointments
- Specialty and Funnel Differences: When to Adjust Benchmarks
- How to Use Benchmarks: Baseline, Target, and Stretch KPIs
- Common Funnel Leaks and Quick Fixes That Move the Needle Fast
- Device Benchmarks: Mobile vs Desktop Conversion in Healthcare
- Regional and Geographic Differences in Healthcare Conversion Benchmarks
- Benchmark Data Across Patient Demographics
- Seasonal Trends and Their Influence on Healthcare Conversion Rates
- Applying Benchmarks in Real Agency Engagements
- How We Help Practices Reach and Exceed These Benchmarks
- FAQ
- Sources
Benchmarks at a Glance: Core Numbers and What “Top Performer” Looks Like
When you ask how your clinic website is doing, the honest answer starts with a range, not a single number. The healthcare sector averages a 5.6% conversion rate across tracked visits, while the strongest performers in the same dataset convert at up to 21.1%. That spread matters more than the average itself. It tells you there’s real room between “typical” and “excellent,” and that room is usually won through better landing pages, faster lead response, and tighter targeting rather than bigger ad budgets.
Separately, broader cross-industry data from Ruler Analytics tracking more than 5 million conversions across 13 industries shows health and social care often landing in the lower single digits on a site-wide basis, depending on how the sample is defined and the time period measured. This is one reason you’ll see different numbers from different reports. Definitions and date ranges change the math.
Here’s a quick-reference range:
- Site-wide average: around 5.6%, per the healthcare-specific benchmark data.
- Top-performer tier: 15% to 21%, representing the upper end of tracked healthcare sites.
- Landing-page performance: typically higher than site-wide averages because the traffic is more qualified and the page has one job.
Percentiles matter because they stop you from comparing your clinic to an unrealistic ceiling or giving yourself credit for hitting a floor. Amplitude’s healthcare benchmarks recommend using the 50th percentile as your baseline, the 75th as a reasonable target, and the 90th as a stretch goal rather than an expectation. That framing keeps your team honest about what “good” means for your specific size and traffic volume, instead of chasing a number pulled from a different kind of practice entirely.
One stat worth sitting with: the gap between average (5.6%) and top performer (21.1%) in the Ruler Analytics healthcare report is nearly fourfold, which means most of the conversion rate difference between clinics comes down to execution, not market conditions.
Benchmarks by Channel: Paid Search, Organic Search, Email, and Direct Traffic
Not all traffic behaves the same way, and benchmarking your whole site as one number hides where your real opportunity sits. Channel intent changes everything about what a “good” conversion rate looks like.
- Paid search tends to convert highest when the ad and landing page are tightly matched to a specific service, because the visitor already typed in something close to “book a consultation” or “same-day appointment.”
- Organic search converts well but more slowly, since a portion of that traffic is still researching rather than ready to book.
- Email performs strongly among existing patients or warm leads, often outperforming cold channels because trust is already established.
- Direct and referral traffic usually sits in the middle, reflecting a mix of returning patients and word-of-mouth visitors who already have some familiarity with the practice.
The reason paid search landing pages so often outperform the rest of the site comes down to message match. A general homepage has to serve every visitor’s intent at once: new patients, existing patients, jobseekers, and referring physicians. A dedicated landing page built for a single Google Ads campaign only has to answer one question for one audience, which is a structural advantage, not a creative trick.
If you’re deciding where to focus first, the channel choice should follow your goal. Practices chasing volume for a new service line often get faster signal from paid search, since you control the traffic and can test landing pages quickly. Practices building long-term patient acquisition at a lower cost per lead tend to lean harder into organic search and content, accepting a longer ramp-up in exchange for compounding returns. Many clinics run both, just not on the same timeline or budget split. We’ll walk through paid versus organic tradeoffs in more detail further down, because the honest answer is rarely “pick one.”
Conversion Types and How Benchmarks Differ: Forms, Calls, and Booked Appointments
A “conversion” means different things depending on what you’re tracking, and that distinction changes which benchmark applies to you. Form fills, phone calls, and actual booked appointments are three different funnel stages, and conflating them is one of the most common measurement mistakes we see.
- Form submissions are usually the easiest conversion to capture and typically the highest-volume action on a landing page.
- Phone calls often convert at a higher intent level than forms, since a caller has already decided they want to talk to someone, not just leave their email.
- Booked appointments are the real outcome that matters, and they’re always a smaller number than total form fills or calls because not every lead converts to a scheduled visit.
Healthcare’s conversion-type mix, per Ruler Analytics, shows forms and calls making up the bulk of tracked conversions, which reflects how most clinics still rely on a phone call or contact form before a patient reaches the calendar. If you’re only tracking form submissions, you’re likely undercounting your actual lead volume, since a meaningful share of patients will call instead of filling out a web form, especially for urgent or sensitive care.
The fix is to normalize everything to one metric your whole team can report against, such as booked appointments relative to visits. This forces forms, calls, and chat conversions into a single comparable number instead of three separate dashboards that never quite agree.
Pro Tip: Track “booked and kept” separately from “booked,” since no-shows can make apparent conversion gains look stronger than the results you actually achieve.
Specialty and Funnel Differences: When to Adjust Benchmarks
Benchmarks shift by specialty because the underlying decision looks nothing alike. A patient booking a routine dental cleaning moves fast and cheap. A patient researching a facelift or a weight-loss procedure moves slowly, compares several providers, and converts at a lower rate per visit even when they’re highly motivated.
- Dental and general practice tend to see higher site-wide conversion rates because the service is familiar, lower-cost, and often urgent.
- Cosmetic and med spa services usually convert lower per visit since the research cycle is longer and price sensitivity is higher.
- Mental health and behavioral care often shows a wide range depending on whether the visitor is in crisis (fast conversion) or exploring options (slow conversion).
- Pain management and specialty clinics frequently see mid-range conversion rates, shaped heavily by insurance questions and referral requirements.
Competitive density plays a role too. A market with many med spas bidding on the same keywords pushes cost per lead up, which usually drags the blended conversion rate down unless the landing page is unusually strong. If you’re in a crowded specialty, use the specialty-adjusted number as your baseline instead of the general healthcare average.
How to Use Benchmarks: Baseline, Target, and Stretch KPIs
Raw benchmark numbers only become useful once you translate them into a framework your team can act on. We recommend a three-tier structure built directly off the percentile data:
- Baseline (50th percentile): your floor. If you’re below this, something in the funnel, usually the landing page or lead response time, needs attention before you spend more on traffic.
- Target (75th percentile): your working goal for the next quarter. This is realistic enough to hit with focused testing, not just more ad spend.
- Stretch (90th percentile): your ceiling for a specific campaign or page, not your whole site. Few practices sustain this across every channel at once.
Before you apply any of these tiers, segment your data. Benchmarking your whole site as one blended number hides where the actual problem or opportunity lives. Break it down by landing page, by channel, and by audience (new versus returning patients) before you decide whether you’re underperforming or right on target.
If a round of testing, tighter message match, a shorter form, and faster follow-up moves that rate to the 75th percentile tier (roughly 12%, based on the top-performer range in the healthcare benchmark data), the same 2,000 visits now produce 240 leads. That’s 128 additional leads a month with zero additional ad spend, just funnel improvement. If even half of those convert to booked and kept appointments at a modest $150 visit value, that’s roughly $9,600 in added monthly revenue from conversion work alone.
Common Funnel Leaks and Quick Fixes That Move the Needle Fast
Most underperforming healthcare funnels share the same handful of problems, and the fixes are usually operational before they’re creative.
- Slow lead response is the single biggest leak we see: a lead sitting unanswered for hours quietly disappears into a competitor’s calendar.
- Fragmented intake across multiple forms, phone trees, and scheduling tools frustrates patients before they ever reach a provider.
- Weak ad-to-page message match sends paid traffic to a generic homepage instead of a page built for that specific campaign.
High-leverage fixes we test first: a one-step booking flow instead of a multi-page form, a dedicated landing page per campaign instead of a shared page, a tightened response-time SLA for inbound leads, and call tracking paired with form analytics so nothing falls through unattributed.
Pro Tip: Appointment-level attribution, not just lead-level tracking, is what finally shows you which channel actually fills the calendar, not just which one fills your CRM.
Device Benchmarks: Mobile vs Desktop Conversion in Healthcare
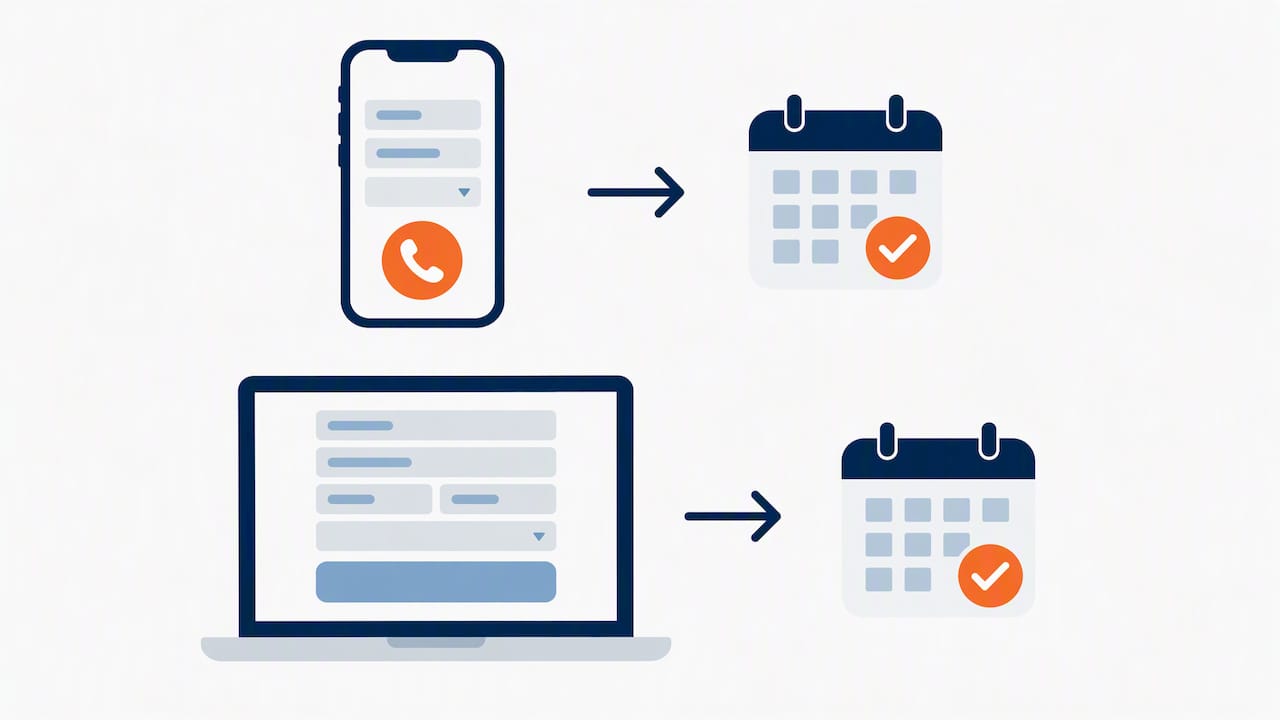
Mobile traffic now makes up the majority of healthcare search visits, but mobile conversion rates typically run lower than desktop, especially for longer forms or multi-step booking flows. Patients browsing on a phone are often still in the early research stage, comparing providers between other tasks, while desktop visitors are more frequently further along and ready to complete a booking or fill out detailed intake information.
That gap narrows considerably when the mobile experience is built for thumbs, not shrunk down from desktop. A mobile landing page with a tap-to-call button above the fold, a short form (name, phone, reason for visit) and minimal scrolling closes most of the performance gap we typically see between devices. Desktop still tends to win on forms that require more detail, like insurance information or multi-field intake, since typing on a phone discourages completion.
The practical takeaway is to treat mobile and desktop as separate funnels with separate benchmarks rather than averaging them together. A site-wide conversion rate that blends both can mask a strong desktop number hiding a weak mobile one, or the reverse. If a substantial share of your traffic arrives on mobile, your mobile conversion rate deserves more attention than a single blended average gives it. Testing a simplified mobile form can be a useful way to identify opportunities for improvement.
Regional and Geographic Differences in Healthcare Conversion Benchmarks
Where a practice is located shapes conversion benchmarks more than most marketers assume. Competitive density varies sharply between a major metro market crowded with med spas and specialists, and a smaller regional market with fewer providers competing for the same search terms. Higher competition usually means higher cost per click and a more price-sensitive, comparison-shopping visitor, which can push conversion rates down even when traffic quality is strong.
Insurance and payer mix also differ by region, and that affects how fast a visitor moves from inquiry to booked appointment. A market dominated by cash-pay cosmetic services behaves differently from one where most visits route through insurance verification before scheduling, and that extra step naturally slows the funnel.
Local search behavior matters too. Practices in areas with strong “near me” search volume often see better-than-average conversion rates on geographically targeted landing pages, since the intent signal is already high before the visitor arrives. Practices in sparser markets may see lower raw volume but higher conversion rates once a visitor does arrive, simply because there’s less competing noise. Rather than benchmarking against a national average, it’s worth comparing your numbers against practices of similar size and competitive density in a similar type of market, not just the same specialty.
Benchmark Data Across Patient Demographics
Different patient populations convert differently, and that affects which benchmark tier is realistic for your practice. Younger patients researching routine or cosmetic care tend to move through a longer digital research phase, comparing reviews and pricing across multiple providers before booking, which can lower top-of-funnel conversion rates even when overall lead volume is healthy.
Older patient populations, particularly those seeking specialty or pain management care, often convert at higher rates once they reach a landing page, since the visit is frequently driven by an existing condition or a referral rather than open-ended research. That said, this population may also rely more heavily on phone calls than online forms, which means a funnel measuring only web-form conversions will understate real demand.
Income and payer type shift behavior as well. Populations weighing out-of-pocket costs for elective or cosmetic procedures tend to take longer and convert at a lower rate per visit, while patients with urgent or insurance-covered needs usually convert faster. None of this means you need a different benchmark for every demographic slice. It means that if your patient base skews heavily toward one group, your realistic target should reflect that group’s typical path, not a blended national number that assumes an even mix.
Seasonal Trends and Their Influence on Healthcare Conversion Rates
Healthcare conversion rates move with the calendar more than most practices plan for. Many elective and cosmetic services see a seasonal lift heading into spring and early summer, as patients prepare for warmer weather or upcoming events, while interest in some services dips around major holidays when attention and discretionary spending shift elsewhere.
Insurance cycles create their own seasonality. Deductible resets at the start of the year can slow elective bookings in January as patients wait to see their out-of-pocket costs, then pick back up once deductibles are partially met later in the year. Specialties tied to seasonal health patterns, like allergy-related care or certain mental health services, see predictable demand swings tied to time of year rather than marketing performance.
The practical implication is that a single month’s conversion rate should never be treated as your permanent benchmark. If you’re comparing performance against a report that pulled data from a slow season, you may think you’re underperforming when you’re actually tracking normally for the time of year. The better practice is to compare year-over-year for the same month, or to build a rolling quarterly average, rather than reacting to short-term dips that are seasonal rather than structural.
Applying Benchmarks in Real Agency Engagements
A common pattern: a clinic with a high raw conversion rate but poor lead quality, versus one with a modest rate but steady, high-value referrals. The number alone never tells the full story. Reliable CRO and paid-search test results take time to read clearly, which is why we build improvement work around frameworks like our 90-day KPI playbook rather than reacting to a single dashboard snapshot.
— Felix
How We Help Practices Reach and Exceed These Benchmarks
Once you know where your numbers sit against these benchmarks, the next question is usually what to fix first, and that’s where we come in. Our conversion rate optimization work typically starts by identifying which stage, whether the landing page, the form, or lead response, is costing you the most leads.
For practices whose main gap is a generic or outdated site, we build custom landing pages designed around message match and booking flow. Current prices are on our pricing page. Practices running paid traffic alongside organic growth often combine landing-page work with our Google Ads management and SEO services to improve both channels at once.
A diagnostic engagement may include:
- A funnel audit comparing your current conversion rates against percentile benchmarks for your specialty.
- A prioritized list of tests on landing page, form length, and response time, ranked by likely impact.
- Measurement setup connecting form, call, and booking data into one reportable metric.
If you want a clear read on where your practice stands, request a benchmark review to assess where the gaps may be.
FAQ
What Is the Average Healthcare Industry Conversion Rate?
The average healthcare conversion rate is 5.6%, with top performers reported as reaching 21.1%. Landing pages built for a single campaign typically convert higher than general site traffic, since the message match is tighter.
What Is Conversion Rate Optimization in a Healthcare Context?
Conversion rate optimization is the practice of testing and improving the elements of a website or landing page, like form length, page layout, and calls to action, to turn more visitors into booked appointments. In healthcare specifically, it often focuses on reducing form friction and speeding up lead response, since both have an outsized effect on whether a lead actually books.
What Is a Referral Conversion Rate?
A referral conversion rate measures how many patients who arrive through another provider’s referral, or through word of mouth, actually complete a booking. Referral traffic tends to convert well because trust is already partially established before the visitor reaches your site.
What National Benchmarks Are Used in Healthcare Marketing?
Healthcare marketers commonly reference benchmark reports that track conversion rates by percentile, such as the Ruler Analytics healthcare report showing a 5.6% average, and Amplitude’s product benchmarks that break metrics down into 50th, 75th, and 90th percentile tiers. These percentile-based frameworks are generally more useful than a single average, since they show the realistic range between typical and top-tier performance.
Sources
Two benchmark reports can show wildly different numbers for the same industry, and the gap usually comes down to methodology, not reality. Before you trust a benchmark enough to set a goal around it, check a few things.
Before comparing your own numbers to any outside benchmark, make sure you have enough stable traffic on a consistent channel to draw a useful comparison. Comparing three days of paid search data against a quarterly industry average will never give you an honest read.
Recommended
- How Many Leads Should A Clinic Expect Per Month From Marketing? → Benchmarks By Budget & City
- What KPIs Matter For A Counseling Clinic? From CPL To Show-Rate Explained
- 90 Day Sprint: Booked Appointment Healthcare Marketing ROI For Clinics
- Double Booking Page Conversion For Clinics With Three Simple Fixes